Table of Contents
Introduction
A patient has completed the forms. The appointment is booked, and the reminder has gone out. But the front desk may still have to check a new insurance card, follow up on an unsigned consent or enter information into the practice record.
For a dental group, this is where patient-access friction becomes visible. A task has moved online, yet someone still has to carry it through to the next step. That work can happen before the visit, during check-in or later, when a payment needs to be reconciled.
The question for DSO leaders is straightforward: where does completed digital work still require staff to repeat, recover or chase it?
Answering that question takes more than counting forms submitted or messages sent. It means following the work across intake, eligibility, scheduling, check-in, communication and payments. CERTIFY Health’s reported dental deployment outcomes, customer interviews and operational reporting provide useful evidence of what changes when those steps connect. Industry research adds context for the administrative work that remains.
Digital intake should reduce the work that follows it
Think about what happens after a patient submits an intake form. Can the team use the information where it is needed? Can staff see what changed? Or do they still have to copy details, scan a document or ask the patient to provide the same information again?
CERTIFY Health’s published customer data describes form completion rising from below 25% to nearly 90%, while phone and email accuracy improved from about 50% to 98%. These are deployment-specific outcomes, but they show why intake quality matters beyond the form itself.
More complete forms give the team more information to work with. Accurate contact details support reminders and follow-up. Together, they create a stronger starting point for preparing the visit. The next operational question is whether the submitted information reaches the practice record and is available to the person who needs it.
Customer interviews describe that change in practical terms. A dental group’s operations team reported being notified when patients updated their information, with the changes reflected in its systems. A revenue-cycle leader described receiving insurance-card information in advance so staff could prepare the patient’s insurance record before the appointment.
That is the workflow to examine when measuring duplicate work. Count the visits where information already supplied had to be entered again, and record why. A changed plan or a new clinical requirement needs review. Repeating a completed step because information did not carry forward is a different kind of work.
Preregistration creates time to resolve what is still missing
CERTIFY Health’s published enterprise DSO data reports 87% overall preregistration completion, including 88% for new patients, 87% for returning patients and 73% among patients over 75. The age-group finding gives dental teams a reason to assess adoption rather than assume older patients will avoid digital intake.
Preregistration completion tells you whether patients completed that workflow. Visit readiness asks whether the applicable forms, consents, identity, coverage and financial requirements were resolved by the time they were needed.
For example, a patient may complete the medical-history form while an insurance question remains open. Another may submit an updated card but still need to sign a consent. The team needs to see the specific unfinished task and know who will act on it.
Set a consistent review point, such as the day before the appointment, and keep same-day bookings separate. Then look at unresolved work by appointment timing and age. A consent needed for tomorrow’s visit requires a different response from an item associated with an appointment several weeks away.
This is where exception ownership matters. The person responsible for resolving a task should be clear, along with the next action and deadline. When a task is reassigned, retain its original opening time. Otherwise, an old problem can appear new each time it moves between teams.
The useful outcome is a front desk that can focus on the patients and exceptions that need attention, with completed preparation already available.
An electronic eligibility response still needs to support the visit
The 2024 CAQH Index, covering 2023 activity, reported dental eligibility and benefit verification at 82% fully electronic, 15% partially electronic and 3% manual. It estimated an eight-minute dental-provider time savings opportunity per transaction from electronic eligibility and benefit verification.
Those findings give historical industry context for reducing administrative effort. They also make the next question worth asking: can the team use the response to prepare for the intended visit?
An electronic exchange can still lead to a phone call or portal review when required information needs clarification. Staff need to know which issue remains, whether it affects the upcoming appointment and who should resolve it. Capturing the insurance card earlier helps create time for that review.
For a DSO, eligibility should be assessed alongside intake and scheduling. Review how often staff must retrieve information again, repeat an inquiry or leave an unresolved coverage question for the day of service. Record the reason for that work so a missing input, an unclear response and a newly changed plan can be addressed appropriately.
The benchmark is useful when it points to a specific operational improvement. An electronic-adoption percentage alone cannot tell you how much follow-up a particular practice still performs.
Patients should be able to continue when they change channels
A patient might begin intake on a phone, call with a question and finish at a kiosk. The handoff should preserve the information already provided and make the remaining step clear.
Reported enterprise deployment outcomes include 80% kiosk check-in adoption across the network. That shows substantial use of self-service at arrival. To understand how well the wider journey works, review whether patients and staff can continue from completed preparation when they switch channels.
Customer interviews describe practices moving away from patients filling out paper packets, staff scanning them and documents being shredded afterward. Digital preparation and kiosk check-in changed that sequence so the team could use information already collected.
A restart occurs when progress is lost or previously completed work must be repeated during the same task. Asking a patient to confirm a changed detail is different from asking them to complete the same packet again. Staff-assisted service is useful when someone needs help; it should continue the existing task wherever possible.
The same principle applies to scheduling. CERTIFY Health’s reported enterprise deployment results include 12,727 new-patient appointments booked without staff intervention and 4,900 appointments filled through waitlist and ASAP workflows between August and December. Both counts describe activity in that deployment.
The ADA Health Policy Institute reported an average new-patient appointment wait of 13.9 days in Q2 2026. That national finding makes cancellation recovery and patient-led booking relevant to access. For each practice, review whether a recovered slot leads into the required preparation workflow, rather than another manual list of calls and forms.
Financial communication should carry through to the practice record
A payment link helps a patient act. The operational work continues until the transaction is reflected correctly and the team knows whether the balance still needs attention.
In customer interviews, a revenue-cycle leader described card payments posting automatically to the dental practice management ledger, removing the need for staff to enter the payment amount again. The same interview described offices gaining visibility into Text-to-Pay, payment-plan, autopay and collection-notice activity.
This is a concrete way to evaluate writeback and reconciliation. Check whether the intended update reaches the correct record, what happens if a transfer is interrupted and how staff can recover an unresolved item. Keep automatic retries attached to the same intended update so one interrupted transfer does not become several separate failures in the measurement.
Published deployment outcomes provide another view of financial engagement. CERTIFY Health reports $110,000 collected through 168 payment plans across 87 clinics over six months, with fewer than 5% cancellations, declines or insufficient-funds events. The finding shows use of a payment option and reported follow-through in that deployment.
Financial outreach also needs to account for channel choice. In aggregate reporting captured September 30, 2026, electronic categories represented 73.16% and paper 26.84% of 81,515 recorded statement categories for January 7 through September 29.
Paper can be the patient’s preferred route or an alternate delivery path. Separate planned paper delivery from recovery after an electronic attempt. Then connect each contact to the balance being addressed. Sending another message, opening a statement and resolving a balance are different events.
That distinction helps teams measure contact attempts and unresolved tasks without treating every additional communication as avoidable work.
Regional differences deserve a closer look than one network average
Standardizing a workflow across a dental group means checking how it operates locally. An enterprise average can help establish direction, but it cannot explain every regional difference.
In one multi-site dental deployment’s September 30, 2026 reporting snapshot, twelve visible regional completion rates ranged from 57.73% to 91.18%, a 33.45 percentage-point spread. The view used appointments from July 2 through October 30 and included remote and kiosk activity. It is a snapshot of recorded completion, including future appointments, rather than a measure of readiness before arrival.
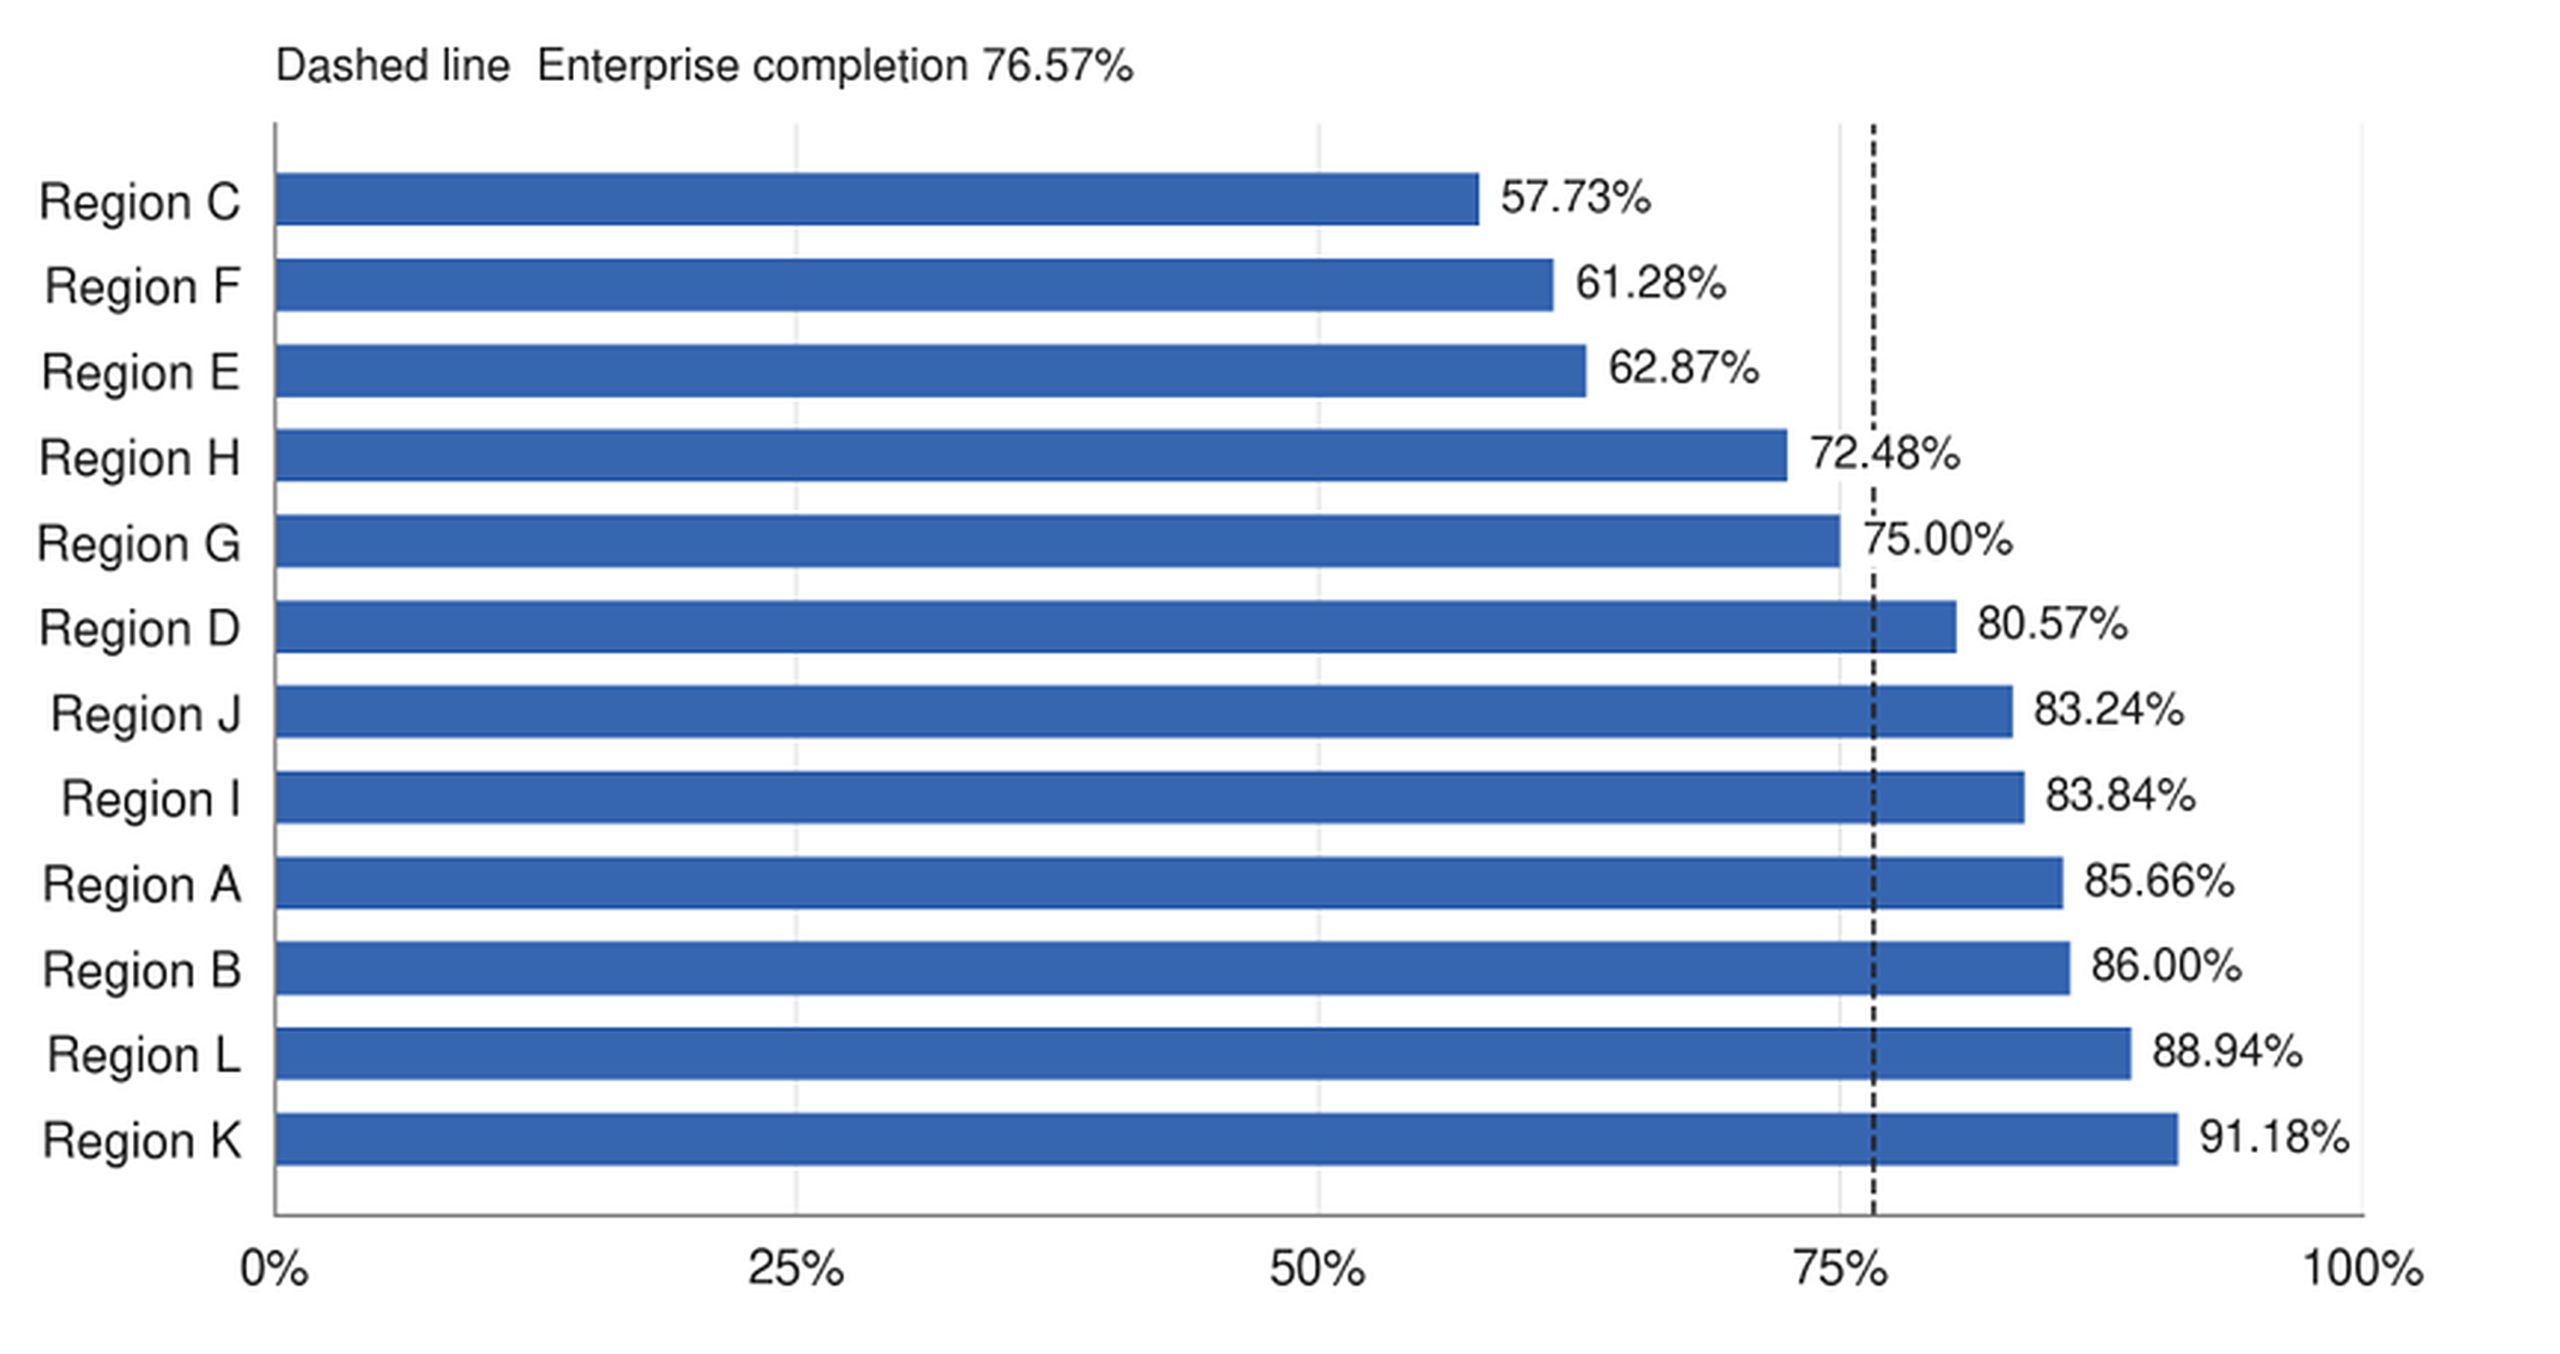
Source CERTIFY Health aggregate operational reporting. Regions are anonymized as A to L. The dashed line marks recorded enterprise completion of 76.57%. Snapshot September 30, 2026; appointment filter July 2 to October 30. Includes remote and kiosk activity.
A lower regional rate identifies where to investigate. Review the same patient type, required forms, workflow version and appointment timing before attributing the difference to staff performance. Contact-data quality, patient needs and rollout timing can affect what the team is seeing.
For ongoing location reviews, retain each site’s completed count and eligible denominator. Calculate the enterprise rate from total counts, then look at variation among comparable locations separately. This keeps a high-volume location from concealing repeated work elsewhere.
Use a benchmark worksheet to start a specific conversation
The reference values below bring the article’s findings together. Compare your practice using the same counting unit and period, and keep deployment outcomes separate from national research. Use each reference to frame an investigation into a comparable workflow.
| Measure | Published reference | Source and comparison context |
|---|---|---|
| Digital form completion | Below 25% to nearly 90% | Reported customer deployment outcome |
| Phone and email accuracy | About 50% to 98% | Reported customer deployment outcome |
| Overall preregistration completion | 87% | Reported enterprise DSO outcome; distinct from full visit readiness |
| Kiosk check-in adoption | 80% | Reported enterprise network adoption |
| Fully electronic dental eligibility and benefit verification | 82% | 2024 CAQH Index, covering 2023 activity |
| New-patient appointment wait | 13.9 days | ADA Health Policy Institute, Q2 2026 national survey finding |
| Payment-plan cancellations, declines or insufficient-funds events | Fewer than 5% | Reported six-month deployment outcome across 168 plans |
| Visible regional completion range | 57.73% to 91.18% | Twelve visible regional rates; September 30 2026 snapshot |
| Electronic and paper statement mix | 73.16% electronic; 26.84% paper | 81,515 recorded statement categories, January 7 to September 29 2026 |
The next step is to examine the work behind the number. If forms are complete but staff still type the same details again, investigate the transfer into the practice record. If a task stays open across several reminders, check its owner and next action. If regional completion differs, review equivalent patient cohorts and configurations before changing the operating model.
For direct friction measurement, count affected visit episodes once in the overall rework rate and retain the reasons. Measure unresolved-task age from its original opening time. Review restarts among journeys that changed channel, and reconcile payments against transactions due to post. These measures connect the patient-facing activity to the work the team actually performs.
Build the workflow around what the next team needs
The evidence gives dental leaders several practical places to start: more complete intake, cleaner contact data, preparation before arrival, patient-led scheduling and payments that reach the practice record. Each improvement matters when the next person can use the work already done.
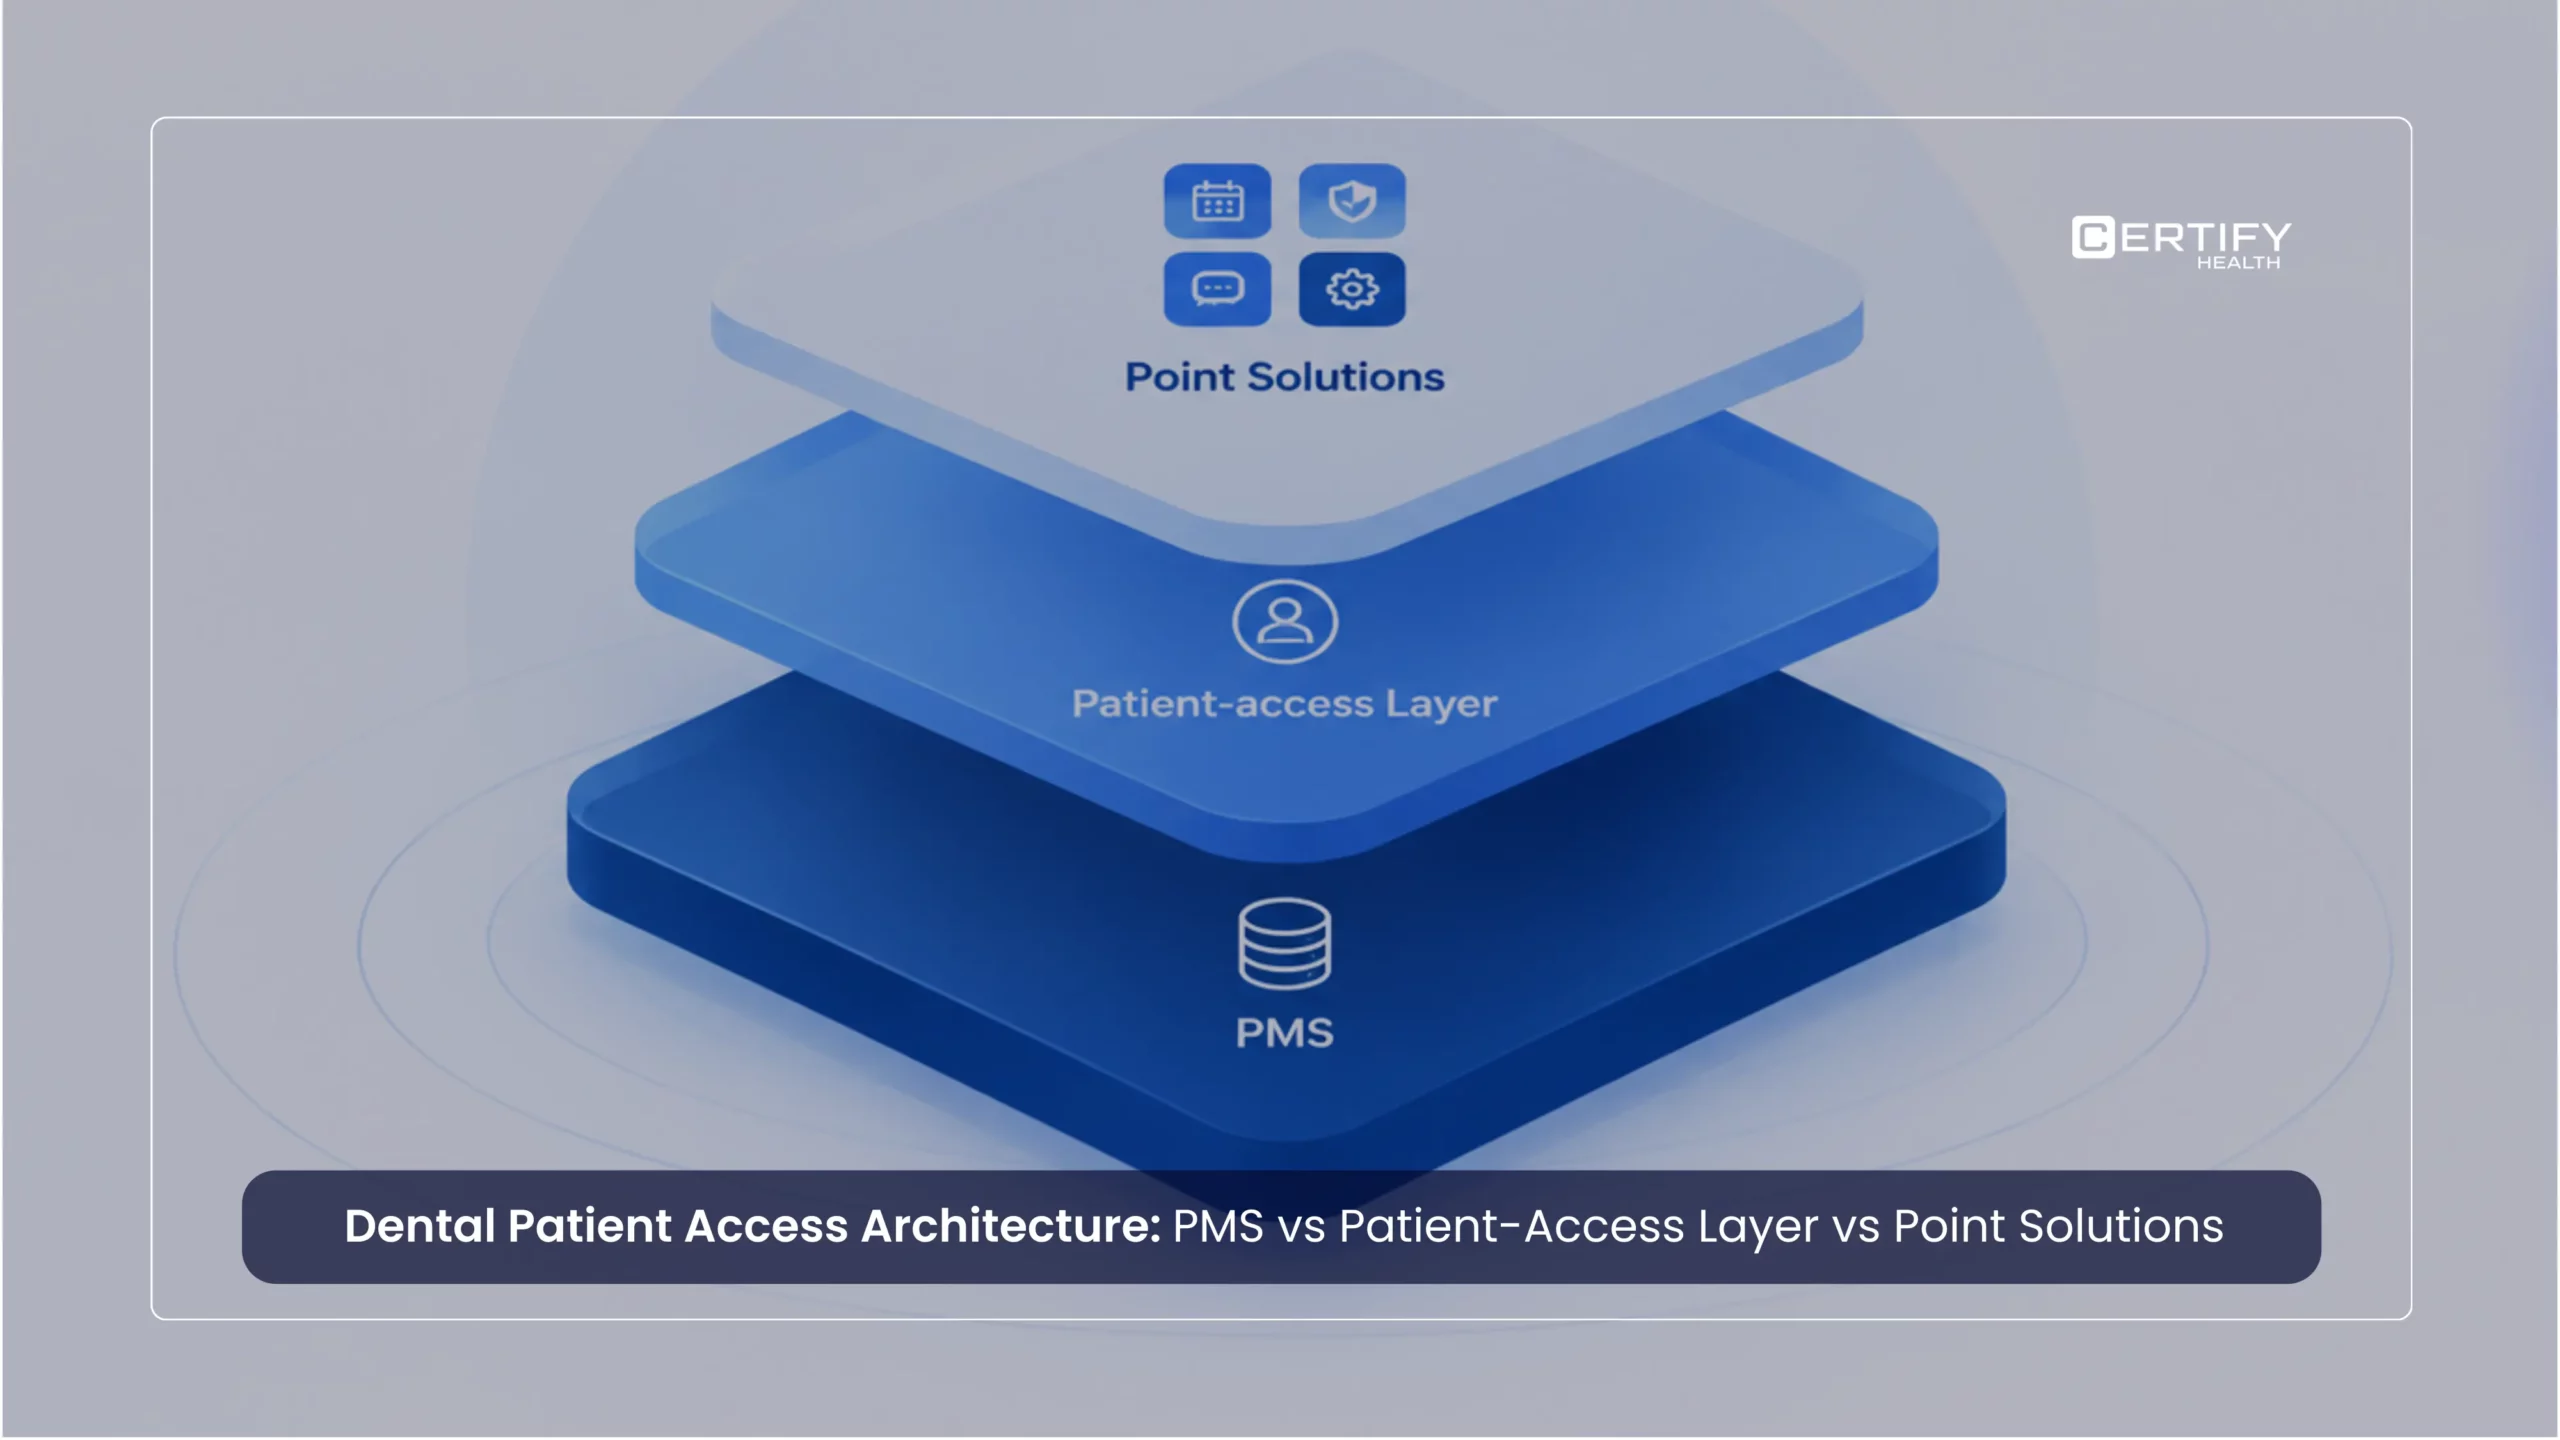
CERTIFY Health connects scheduling, digital intake, eligibility, check-in, patient communication and payment workflows around the organization’s existing practice management or EHR environment. Intake-progress visibility, patient messaging and transaction reporting help teams review what is complete and what needs attention. The information exchanged follows the configured implementation.
For your next review, follow one patient journey from booking through the final payment update. Identify where the patient or staff had to repeat a completed step, where an exception waited and where the next team lacked the information it needed. That gives you a specific workflow to improve and a measure to revisit afterward.
Talk to CERTIFY Health about your dental patient-access workflow.